
My birth story as a Mum with type 1 diabetes
In early February, I gave birth to my beautiful baby boy, Max. He was healthy, and I ended up with the birth I really wanted - not a guarantee given the capricious and unpredictable nature of bringing new life into the world.
In early February, I gave birth to my beautiful baby boy, Max. He was healthy, weighing 8lbs 2oz (3.7kg) and I ended up with the birth I really wanted - not a guarantee given the capricious and unpredictable nature of bringing new life into the world.
And after many anxiety-inducing months of navigating a ‘high risk’ type 1 diabetes pregnancy, I was beyond relieved to have him here, and for him to be well. Whilst overall my experience was a positive one, there were plenty of twists and turns to keep us on our toes, and a fairly difficult postnatal experience in hospital - more on that below.
For now, he’s here, and 8 weeks down the line, I want to document what happened, as a personal journey for myself (that we did it!) but also to serve as a hopeful reassurance that women with type 1 diabetes can have healthy babies, and can get the birth they wish for.
Buckle up, it’s a chunky one.
Antenatal concerns
To begin, we need to start in January, a few days after the new year, and me well into my third trimester. I’d been back and forth to the triage and antenatal clinic. My insulin requirements had dropped a fair amount in the last 4 weeks of pregnancy. This isn't expected. Usually you’re busy chasing down highs due to increasing resistance. As the placenta is responsible for providing the hormones that cause insulin resistance, there were concerns that my placenta was ageing too much or too quickly, and wasn’t working well enough to provide the baby with all the nutrients and oxygen he needed. This is more likely to happen if you have type 1 diabetes.

Overnight stay at triage featuring very sexy compression stockings (& lots of Bridgerton)
That being said, the frequent growth scans showed good blood flow between my placenta and the baby, and the baby was growing in line with what was expected. It was hard to understand the shift in insulin requirements, and plethora of hypos.
During one of my final antenatal appointments at 36 weeks, due to concerns around hypos and lower insulin requirements, in the room with me I had two obstetricians, 1 DSN, 1 diabetes consultant, 1 midwife, and a diabetes dietician, all trying to fathom what could be going on. Despite the stress, this was a really useful appointment as it truly felt like collaborative care between me and the medical professionals. My insights were just as useful for developing a plan that felt good for all of us. Though none of us could really work out what was happening.
Due to the stress and concerns around the pregnancy (at one point, there was talk of delivering there and then), my blood pressure spiked high. Not uncommon to happen during stressful times, but due to my history of developing pre-eclampsia during my last induction, and the increased likelihood of high BP in T1D women, I landed myself an overnight stay in the triage ward. I started on the first line treatment for hypertension in pregnancy (a medication called labetalol) and settled in for 4-hourly observations. Babe was monitored on the CTG and he looked happy and content.
My BP seemed to stabilise with the medication, and a calmer nervous system. In the morning I was sent home, but recommended to start the induction sooner than planned. Not completely unexpected, and frankly welcomed by me after all the ongoing uncertainty.
Induction
On Sunday 8th at 4pm, I was admitted to the induction ward. The midwife looking after me had a special interest in type 1 diabetes, which automatically put me at ease and honestly makes all the difference to hospital care. We talked through different induction options. I’d used the hormonal pessary with my first induction, and was keen to go for this again. Even though it hyper-stimulated my cervix and caused some issues with back-to-back contractions, I was willing to overlook that because it got the job done.
However, it turns out my keen bean cervix wasn’t a fluke. The hormonal pessary is known to hyper-stimulate and cause problems. Given my history, my midwife dissuaded me from the pessary and recommended the cook balloon instead. This involves attaching two balloons filled with saline to your cervix and vaginal. It’s non-hormonal and uses gravity to irritate the cervix into action - so more reminiscent of a spontaneous labour.


At 6pm, and with a healthy dose of gas and air, the cook balloons were inserted (the least fun kind of balloon, as my friend texted me, in sympathy). Now I had to wait for 24 hours, or for the balloons to fall out, whichever came first. I was told to keep mobile and positive, cue lots of bouncing on a pregnancy ball and lots of baths. I also roped my husband into daily back massages to keep my hypertension at bay. So far so good.
Overnight, I started to feel some tightenings and discomfort and was getting excited, but by 6pm the next day, the balloons were still in place and they had to be manually removed. I was only 2cm dilated. The next step on the intervention pathway was to break my waters, but I needed a room on the delivery suite for that to happen. So we hunkered down for another 24 hours on the induction ward (more massages, baths…so wasn’t all bad).
By 10.30pm the following day, after a listless day of waiting and much money spent in the hospital’s M&S, we finally got the green light to head up to the room where I’d give birth. Once there, we discovered there were some concerns with the baby’s positioning. He was still high (didn’t my ribs know about it), so they recommended performing a controlled rupture of the membranes. This meant having two midwives present. One to break my waters and the other to push down on my stomach, encouraging the baby's head to descend before the umbilical cord could (it’s rare for the cord to get there first, but if this happens it’s a medical emergency).
Given the busyness of the ward, we had to wait until 3am for this to happen. Not a problem as it allowed us to rest a bit, though of course, I was too nervous to settle.
As soon as the waters were broken (basically with a big hook that looks like a knitting needle - nice) my contractions really ramped up. They were coming every 90 seconds to 2 minutes. It was undeniable that things were progressing now.
Active labour
I used breathing techniques and pacing around the room to manage for the first hour or so, but I felt quite out of control with how quickly things were happening. My midwife was fairly hands off, and she spent a lot of time sat in the corner taking notes. I guess I wanted more encouragement and reassurance from her, but in the moment couldn’t find a way of communicating this.
I started using gas and air, and my plan pre-induction was to use this throughout, as I had done with my first labour. But this time, and probably because I necked it all a bit too quickly, the gas made me nauseous and I started to vomit. I panicked and started to doubt I could do labour if my pain relief option wasn’t viable.
Despite the intensity of the birth, diabetes-wise things were looking incredibly smooth. I was managing using the CamAPS system (hybrid closed loop pump - more on those here). I was fully prepped with hypo treatments (Lift shots), and was ready to hit the Boost function as soon as necessary. I’d given my husband a crash course in t1d management, so as well as being my birth partner, he was also my assistant pancreas. Hats off Eddie!
But as it turns out, I didn’t need to do any of those things. Yes, the irony of diabetes pushing me into the ‘high risk’ category but causing me no problems is not lost on me.
I managed a few intense rounds of contractions before requesting a vaginal exam. I was 5cm. This was a blow. I felt much further along - maybe wishful thinking? - but I guess it brings up a valid discussion of how useful exams can be. 5cm knocked my confidence. I felt way more than 5cm. So I decided to opt for an epidural. Luckily for me the anaesthetist came quickly, but it took longer than expected to insert. The contractions were coming so quickly, so we had to wait until they passed for the doctor to insert the catheter into my back. Finally it was in and I could move positions.
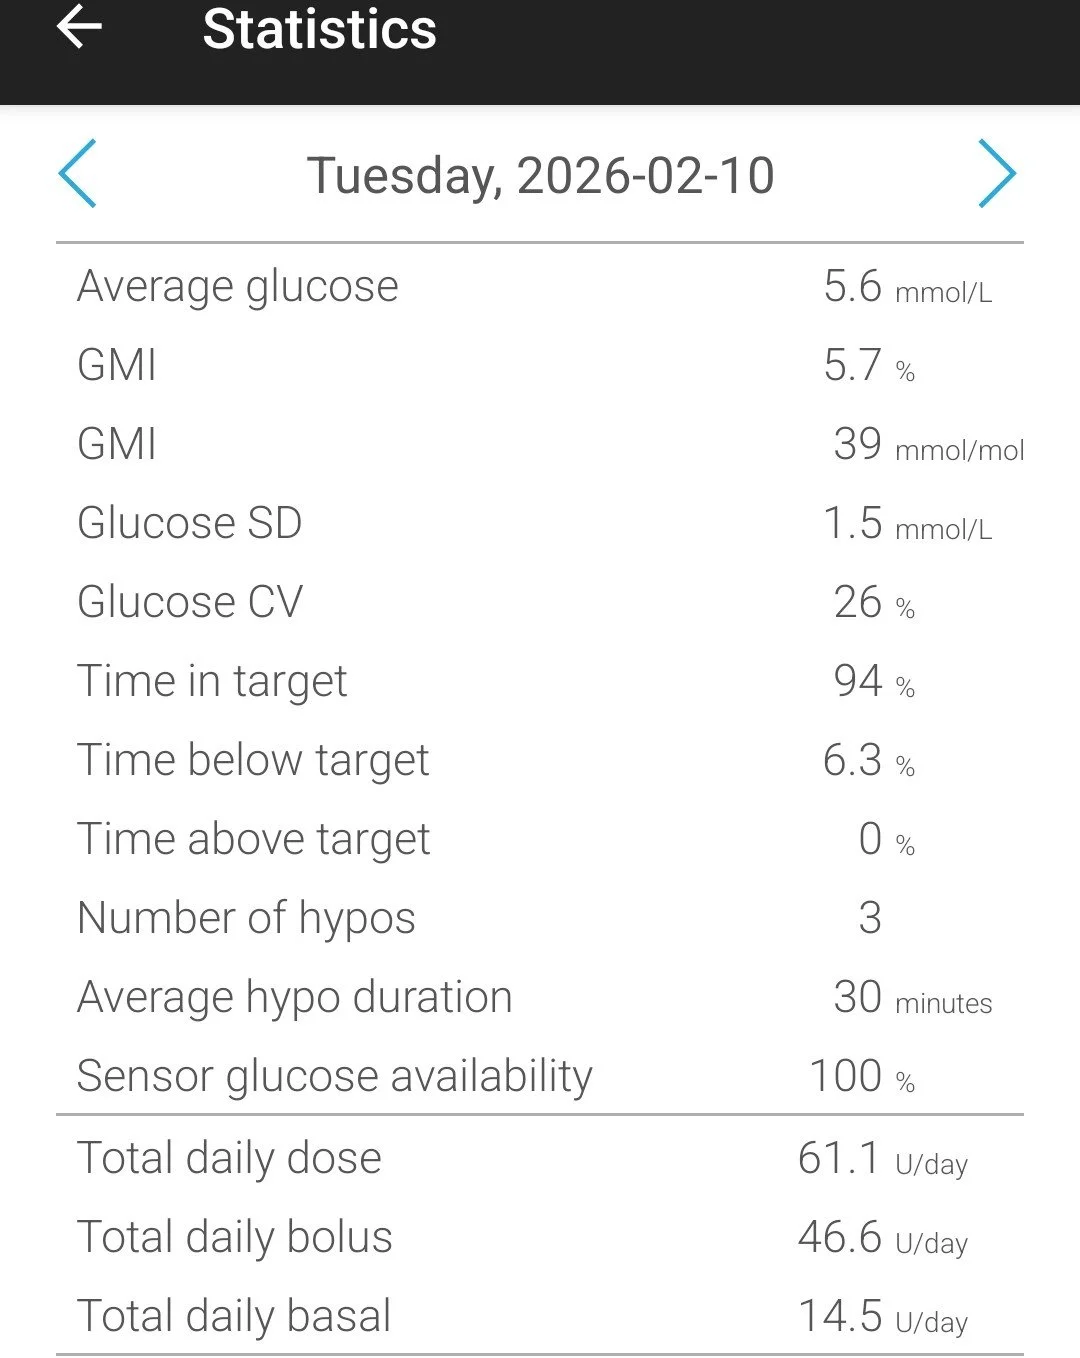
Stats from my pump the day Max was born
now push it🧡
push it real good 🧡
now push it🧡 push it real good 🧡
Time to push
Time gets very hazy here, for both me and my husband, but it felt like the process from epidural insertion to feeling the urge to push was a blink of the eye. A more senior midwife entered the room at this point, I think at the bequest of my midwife, not me, but I was happy she was there. She was assertive, and direct, and she could see that I was ready to push. She asked to examine me, announced I was 9.5cm, and that as I’d had a baby before, ‘could push the rest of the cervix away’. This kind of matron-esque, no-nonsense vibe was just what I needed.
She helped me get into the best position and talked to me calmly and clearly.
My baby was still high up, and he didn’t like the position he was in. A subtle yet powerful message - you need to act.
I remember the intensity of pushing and gritting mg teeth - no idea how long this went on for. I struggled to feel him move down, maybe due to the epidural, but he made his way. Two more midwives came in. It was the morning handover. I was happy for them to be there, I wanted that cheerleading.
I remember someone suggesting I boost the epidural and then that was it, I gave another push and his head was out. There was quite a reprieve before his body followed, and I found that time odd. The midwiveskept saying how close I was, and encouraging me to go again. I felt like I was miles from the finish line, even though I could feel his head. I turned to my husband for the truth. And he smiled, held my hand, and said, you’re almost there.
That was all I needed before I went one more time, and at 7.38am, about 4.5 hours of active labour, Max was scooped up and placed onto my chest.
We had a beautiful golden hour together. Unhurried, calm, peaceful. The cord was only cut once it had stopped pulsating. We had our first breastfeed. I birthed the placenta.
Side note on the placenta - it was huge. Something I found out later, is that T1D women grow large placentas which have fewer blood vessels than any other pregnant group. This is called hyperplacentosis. It’s also why 150mg of aspirin is prescribed - to reduce the amount of platelets in circulating blood so that those fewer vessels get as much blood as possible. It’s also why our babies be plethoric - have more red blood cells - and are prone to jaundice.
Postpartum care
Max’s blood glucose levels post-birth were always fine. There can be a risk of babies’ glucose being low due to the insulin they’re exposed to from Mum. But as is standard care, his levels were checked for 24 hours post birth. I felt good, minimal blood loss and a few stitches that I didn’t feel due to the epidural. We got moved to a private bed on a transitional care ward. This is a special ward, a step down from NICU, for babies and mothers who are seen as high risk.
I loved this ward. True continuity of care, lots of support, privacy and space.
After 24 hours, Max got discharged, but due to an abnormal kidney function test result, I wasn’t cleared to leave. So we stayed in for another 24 hours. The next day, my bloodwork was fine, but Max developed jaundice (see above point re. placenta). I was heartbroken. Even though it’s very common, I felt as though he wasn’t getting enough food from me to flush out the bilirubin. There are different levels of jaundice and Max reached the threshold for phototherapy treatment. This required him to be in a hospital incubator for 24 hours, so blue-green light could be shone on him to break up the excess bilirubin. He was only allowed out every 3 hours for feeding, and feeds should last no longer than 15 minutes, to maximise the light exposure.
At the same time, someone with greater need than us needed our room, so we got moved to the standard post-natal ward. We found ourselves on a busy and noisy 6-bed bay, sleep deprived, with an inconsolable baby that we couldn’t console. At this point, my husband became invisible too. I found the phototherapy treatment hard to go through, and it gave me a very very tiny insight into how agonising it must be to have a baby on the NICU. The medical team around me didn’t really understand my distress. As far as there were concerned, they’d diagnosed the problem, and had set up the correct treatment to fix it. I didn’t need to be upset.
Being on this ward took me straight back to the postpartum experience I had with my first child, which was arguably one of the toughest times of my life. I had pre-eclampsia and my son was poorly. So on paper a lot more challenging than this labour and postpartum, but my body didn’t seem to distinguish between the experiences. I guess because the lights, the noise, the busyness of the ward, the worry, all took my nervous system right back. The hypertension that up until that point was being managed successfully on medication, soon went out of control and no longer responded the the meds.
I ended up being on the postnatal wards for 8 days, as we all tried to manage the high blood pressure. Luckily, by the final few days, I’d got my own private room, and most midwives knew me pretty well, so at least I developed my own continuity of care by sheer dint of being there so long. The medics increased my dose, changed my medication, added in more medication, but still, as soon as I heard that blood pressure machine wheeling its way down the corridor to me, my body panicked and my BP increased. I was under 4-hourly observations, and I needed to have at least 24 hours of reasonable blood pressure readings before I could go home. This task seemed Sisyphean.
But, after the support of a really great midwife and doctor, on a soggy, grey February afternoon, a whole 10 days after being admitted to hospital, we were given the green light to go home.



Reflections
I feel immensely grateful that I had the birth I wanted. I feel so lucky that my son was, and is, healthy. I feel grief that the beginnings weren’t what I wanted. I’d hoped the postpartum experience would heal the trauma from my first child’s birth, and it didn’t. I had to sacrifice part of our breastfeeding journey so I could concentrate on managing my blood pressure. I ached for my first-born child too, as we’d never been apart that long before. As someone who doesn’t live her life feeling ‘high risk’ being seen through this lens is always tough. Undergoing regular blood pressure checks that told me how poorly I was every 4 hours, was sobering and jarring. I don’t see myself as sick, fortunately.
But despite the twists and turns, I am well and I feel well. Above all, I’m proud, and I hope I’ve shown you that you can have a positive pregnancy and labour experience with type 1 diabetes. Maybe even your positive experience is not despite type 1, but because of it.
If you have any questions or comments, I’d love to hear them! Let me know below.
The T1D Pregnancy Companion
A thorough guide that meets you wherever you're at on your type 1 diabetes fertility journey
The T1D Pregnancy Companion
ALSO - if you’re reading this and hope to have your own t1d pregnancy, but feel overwhelmed, I’ve developed a resource for this exact this moment in your health journey.
To replace fear with facts, and confusion with confidence.
It's a thorough guide that meets you wherever you're at on your type 1 diabetes fertility journey.
Full of evidence-based recommendations, practical interventions, and a toolkit that looks after your mind just as well as it looks after your time in range.

Why join Reset + Rebalance – 3 mini client journeys
Curious about Reset + Rebalance, the 3 month 1:1 programme of targetted nutrition and psychology support that helps t1ds rewrite their management and find peace in the messy of t1d life without resorting to restriction or losing their sanity? Learn why it works and hear from some of the folks who have already worked through the programme.
Curious about Reset + Rebalance, the 3 month 1:1 programme of targetted nutrition and psychology support that helps t1ds rewrite their management and find peace in the messy of t1d life without resorting to restriction or losing their sanity?
Learn why it works and hear from some of the folks who have already worked through the programme.
Stella*
Main issue or challenge:
Stella initially reached out to me as she was struggling to control her blood glucose levels, despite being very vigilant at checking, correcting, and carb counting. She said she wasn’t receiving much support from her healthcare team, and so was interested in my 1:1 offer. She didn’t feel she was getting good quality sleep as she’d often wake overnight with hypos, which she’d then rebound high with. She was also experiencing some health anxiety around long-term complications from type 1. She was also experiencing IBS-like symptoms and reactions to specific foods, though medical tests had all come back inconclusive.
What we worked on:
Digestive health: including focused food monitoring and symptom tracking, slowly increasing soluble fibre, identifying food triggers whilst retaining as many foods in the diet as possible, adding in specific foods and supplements to support the mucosal lining of the gut.
Psychological tools to reduce health anxiety and focus on acceptance around the type 1 diabetes.
Ran thorough blood tests to understand key nutrient levels and biomarkers of t1d health, immunity, and inflammation.
Reviewed CGM data together to spot patterns, especially around menstrual cycle hormonal shifts.
Modulation of the stress response: targetted foods and nutrients, lifestyle factors, and out of sessions homework.
By the end of the programme:
Stella’s HbA1c and cholesterol level had come down, and her time in range went from 50 to 81%.
She says, “for the first time in years my HbA1c has come down! It has stubbornly been stuck at 54 for the last few years, and is now 50. My cholesterol has also come down from 5.3 to 4.5. I told the nurse about your work and how it's really helped my diabetes understanding and management.”
She also saw an improvement in the gut symptoms she was experiencing. After daily stomach aches and bloating, she was symptom-free by the end of our work.
“I have loved working with Beth! After each of our sessions she provided me with such detailed food plans, and has helped me to manage my blood sugar levels. I now have such a better understanding of my body, and my time in range has improved. I'm so glad I came across Beth - she's so knowledgeable, helpful, and friendly, and I really enjoyed all our sessions together.”

2. Julie*
Main issue or challenge:
Julie came to me presenting with diabetes distress. She was guessing insulin doses, not able to weigh food, and not wanting to go hypo so purposefully ran high. She had been misdiagnosed as type 2, and despite managing her glucose levels with food and weight loss, she suspected this was an incorrect diagnosis. 6 years later, when she experienced DKA, she was re-diagnosed as having LADA (Latent Autoimmune Diabetes in Adults, also known as type 1.5). She also had a diagnosis of Hashimoto’s, had found herself in a pattern of yo-yo dieting, and wanted to get on top of her health again.
What we worked on:
Practical tools to support optimal meal planning, preparation, and regular eating, including anticipating stumbling blocks and co-creating proactive strategies.
Healing her food relationship: cultivating the ceremony of food, understanding which foods Julie liked to eat and finding ways to make this possible with her glucose management.
Dialling down inflammatory processes: that were most likely driving her insulin resistance, and other autoimmune conditions.
Optimising her insulin sensitivity: through gentle nutrition, mindful movement, and targetted nutrients.
Uncovering nutrient deficiencies via testing: correcting these deficiencies whilst also unpicking the route cause, and supporting optimal digestive processes to ensure adequate absorption of nutrients.
By the end of the programme:
At the beginning of our work, Julie’s HbA1c was in the 90s. When she emailed an update a few weeks after our sessions ended, this is what she said, “I have dropped my HbA1c from 90 to 66, I have lost 9kg, and my blood pressure is now 127/72 without meds.”
She’d also made some really positive life decisions too, which reduced her overall stress levels, and helped her prioritise what was meaningful to her.
“Beth is amazing. I was diagnosed with LADA in 2020 and have really struggled with controlling the diabetes, weight gain, self-esteem and further autoimmune diseases. I worked with Beth over the 12 weeks to look at getting all the ducks in a row. She was motivating and positive, taking time to think about me holistically. I had a number of life challenges and health issues during our time together and she helped me to navigate through this and the impact on my blood glucose levels. By the end of our time together my confidence has grown, my HbA1c and time in range has improved and I have learned ways to manage this. I still have more work to do, I think T1D never stops needing work, but Beth has started me on my way. The best decision I have made to look after myself - working with Beth!”
3. Mary*
Main issue or challenge:
Mary was referred to me by another practitioner. She had a recent diagnosis of T1D, and felt at a complete loss as to what she should and shouldn’t eat, and wanted support with her nutrition, exercise, and work/life balance. She was menopausal, had recently moved house, had slightly raised cholesterol levels, and had just come out of hospital after an emergency admission due to acutely infected gallbladder with large stones. She was also experiencing very loose stools and urgency to go to the loo.
What we worked on:
Balanced plates for each meal: ensuring all 3 macronutrients were present with her main meals.
Adopted an anti-inflammatory Mediterranean style of eating: for overall health, and recovery post t1d diagnosis.
Supported liver and gallbladder health: to promote optimal bile production and flow, and to optimise detoxification pathways in light of the gallbladder stones.
Managed cholesterol levels: through increasing soluble fibre, adding in a targetted clinical-grade probiotic, focusing on omega 3 sources, and adding in vitamin C-rich foods.
Nutritional education: specifically around carbohydrate counting, tips and tricks to make this easier, the glycaemic load of foods, food pairing to slow down carbohydrate absorption, and more!
By the end of the programme:
Mary felt so much more confident in not just her t1d health, but managing her digestion, and supporting her gallbladder. Her stools were more formed and she wasn’t rushing to the loo anymore.
She said, “thank you SOOOOO much for all the help you’ve given me over the past few months. I feel so very lucky to have found you - I couldn’t have wished for a better person to help me in my ongoing journey with T1D and nutrition.”
She was more able to engage in the healthcare system too, understanding what would be checked as part of her diabetes annual review, and discussing options around a carbohydrate-counting course like DAFNE.
“I cannot praise Beth enough for her expertise, wisdom and knowledge on all things nutritional and T1D. I feel blessed to have found her - she has helped me immensely and it has been an absolute joy to work with her and I would like to have her in my top pocket forever - she is a superstar!”
*client names changed to maintain confidentiality.
And there you go! 3 in-depth client stories that highlight the breadth and depth of this work. Come and Reset + Rebalance with us!
Enjoyed this article? Sharing on socials would be a big thank you!

Why you should up your antioxidants if you live with type 1 diabetes
Why do people like me (nutritionists!) always bang on about these little powerhouse compounds?

What’s the deal with antioxidants?
Why do people like me (nutritionists!) always bang on about these little powerhouse compounds?
Let me explain.
There's a balance between oxidants and antioxidants inside our body.
Oxidants – are produced due to oxidative stress and include things like Reactive Oxygen Species i.e. free radicals, which you’ve probably heard of.
Oxidative stress in the body can be caused by things many things i.e. micronutrient deficiencies, pollution, immune responses to an infection, high and low blood sugars (this is pertinent!).
Oxidative stress can be balanced out by our own internal antioxidant system and antioxidants we eat.
Antioxidants – compounds that can protect your cells from damage caused by potentially harmful molecules known as free radicals (think of them as coming along and ‘mopping up’ the free radicals).
If you live with T1D, it’s impossible to keep your blood sugars in range ALL THE TIME – you will have some highs and lows. That’s why it’s important to get lots of antioxidant-rich foods into your diet.
Antioxidants = fruits and vegetables! Specifically, phytonutrients found in the pigmentation. This is where eat the rainbow comes from (a cliché, but you can see why now!)
Aim to get as many different colours as possible
Red (apples, tomatoes, radish)
Orange/yellow (carrots, mangoes, turmeric, papaya, sweetcorn)
Greens (spinach, sprouts, watercress, broccoli, peas)
Blue/purple (blueberries, beetroot, aubergine, grapes)
White/black (cauliflower, coconut, parsnips, black garlic)
Which colour are you going to focus on this week?

How to manage your T1D in the heat
Feeling hot, hot, hot - how to manage your diabetes in the summer heat.
Beth Edwards Nutrition | Type 1 Diabetes Nutritionist | London Nutritionist | How to manage type 1 diabetes in the heat
Has the heat got your type 1 diabetes hot under the collar?
Lots of my type 1 diabetes clients are noticing differences in their blood glucose levels now the temperatures have started to rise. Maybe you are too?
So what's going on? Well, it all comes down to PHYSICS. The extra heat increases the kinetic energy of the particles in our bodies and our insulin. This provides more kinetic energy (i.e. the insulin moves around quicker and therefore does its job quicker). Additionally, the heat expands your blood vessels, which in turn can speed up insulin absorption and possibly lead to lows.
What can you do?
Keep a close eye on BG levels. If you're dropping low across the whole day, you might need to reduce your background (basal) insulin.
Maybe you find you go higher in the heat. This could be due to your insulin overheating. Ensure you keep your pens and vials in cool, shady spots when out and about, and change your infusion sites (if using a pump) more often if you feel your insulin reservoir is getting too warm.
Always carry lots of water with you, particularly if you're running a little bit on the high side. When the body is dehydrated, BG becomes more concentrated due to the decrease in blood flow through the kidneys. This makes it harder for the kidneys to remove any excess glucose from urine.
It's extra important to keep hypo treatment on you if you know you're prone to going low in the heat.